Categories Neuropathic Pain

Shingles and Nerve Pain: When Does It Become Post-Herpetic Neuralgia?

Shingles and nerve pain showing persistent pain that may develop into post-herpetic neuralgia after the rash clears

Quick Answer

Shingles pain is generally reclassified as post-herpetic neuralgia (PHN) once it persists for 90 days (3 months) or longer after the shingles rash first appeared. Pain that fades within a few weeks, as the rash heals, is considered part of the normal course of shingles. Pain that lingers well beyond that point — especially if it’s burning, stabbing, or triggered by light touch — is the hallmark of PHN, the most common complication of shingles, and is a reasonable point at which to seek focused pain-management care.

Quick Summary

  • PHN is most commonly defined as dermatomal pain lasting 90 days or more after the shingles rash begins.
  • Roughly 1 in 5 people who get shingles develop PHN, with risk rising sharply after age 50–60.
  • Key risk factors include older age, more severe acute pain, extensive rash, pain before the rash appeared, and a weakened immune system.
  • Starting antiviral medication within 72 hours of the rash appearing, and the recombinant zoster vaccine, are the two most evidence-backed ways to reduce risk.
  • First-line treatment is medication-based: gabapentinoids, tricyclic antidepressants, and topical lidocaine or capsaicin.
  • When medication alone isn’t enough, interventional options such as nerve blocks, targeted epidural injections, and radiofrequency-based procedures are established next steps.
  • PHN often improves with time, but pain that has persisted for many months is less likely to resolve on its own and is a reasonable trigger for a pain-specialist evaluation.

Introduction

Shingles (herpes zoster) is well known for its painful, blistering rash — but for a meaningful share of patients, the pain doesn’t end when the rash clears. When nerve pain continues in the same area long after the skin has healed, it has a name: post-herpetic neuralgia (PHN), the most common lasting complication of shingles. The challenge for many patients is knowing where the line falls — how much lingering discomfort is a normal part of healing, and at what point it becomes a distinct condition that benefits from its own treatment plan. This article walks through that timeline, what’s happening to the nerves underneath the skin, who is more likely to be affected, and the treatment options available, from first-line medication to interventional pain procedures.

How Shingles Pain Normally Progresses

Shingles pain typically moves through recognizable stages, and understanding them is the most useful way to answer the “when” question in the title of this article.

  • Acute phase (roughly the first 30 days): Pain accompanies the active rash — from the days before blisters appear (the prodrome) through crusting and healing, generally 2–4 weeks.
  • Subacute herpetic neuralgia (roughly 30–90 days): The rash has usually healed, but some patients continue to have pain in the same dermatome. This phase is a waiting period — pain here has not yet met the clinical threshold for PHN, and for many patients it will continue to fade.
  • Post-herpetic neuralgia (90 days and beyond): Once dermatomal pain has persisted for 90 days or longer from the onset of the rash, it is classified as PHN. Some pain specialists further describe PHN as “well established” once it passes the 180-day mark, since the likelihood of pain resolving on its own drops meaningfully beyond that point.

In practice, this means a patient whose pain is easing week over week, even if it hasn’t fully gone at 6 weeks, is likely still within a normal healing window. Pain that is unchanged, worsening, or newly severe at the 3-month mark is the pattern most consistent with PHN.

What Is Post-Herpetic Neuralgia?

Post-herpetic neuralgia is chronic nerve pain confined to the same band of skin (dermatome) where the shingles rash occurred — most often the trunk, but sometimes the face, neck, or scalp when the ophthalmic or trigeminal nerves are involved. It results from nerve damage caused by the varicella-zoster virus as it reactivated and traveled along the affected nerve. Patients commonly describe the pain as:

  • A constant burning or aching sensation
  • Sharp, stabbing, or electric-shock-like jabs
  • Allodynia — pain triggered by things that shouldn’t hurt, such as clothing brushing the skin or a light breeze
  • Itching or numbness in the same area, sometimes alongside the pain rather than instead of it

Why Shingles Pain Turns Into PHN

The varicella-zoster virus — the same virus responsible for chickenpox — lies dormant in sensory nerve ganglia after a person’s original chickenpox infection. When it reactivates as shingles, it travels along a sensory nerve to the skin, causing the characteristic rash and inflaming and damaging nerve fibers along the way. In most people, these fibers recover as the rash heals. In others, the damaged nerves continue sending pain signals to the brain even after the skin has healed completely — a phenomenon linked to central sensitization and altered nerve-fiber signaling. This is why PHN pain is confined to the exact area the rash covered, and why it can persist long after there is nothing visible left on the skin.

Who Is More Likely to Develop PHN?

Not everyone who gets shingles develops PHN — current estimates suggest roughly 1 in 5 do, though published rates vary with the definition used and the age of the population studied. The clinical literature consistently points to the following risk factors:

Risk FactorWhy It Matters
Older age (especially 60+)The single strongest predictor; risk rises steeply after age 50 and climbs further with each decade.
More intense acute painGreater acute pain is linked to more nerve-fiber damage and a higher chance of persistent pain.
More severe or extensive rashReflects greater underlying nerve involvement at the time of infection.
Pain before the rash appeared (prodrome)May signal earlier, more significant nerve involvement, especially when accompanied by fever.
Immunocompromised statusConditions or medications that lower immune function are linked to higher PHN risk.
Ophthalmic (facial) shinglesInvolvement of the nerve serving the eye and forehead is associated with a higher likelihood of lasting pain.

Signs Your Pain May Be Turning Into PHN

It’s reasonable to keep an eye on shingles pain rather than assume the worst, but a few patterns are worth paying attention to:

  • Pain that hasn’t meaningfully improved by 8–12 weeks after the rash appeared
  • Pain that is burning, stabbing, or electric-shock-like rather than a dull soreness
  • New sensitivity where even light clothing or a gentle touch causes pain
  • Pain confined strictly to the area the original rash covered

How Is PHN Diagnosed?

PHN is generally a clinical diagnosis — there is no blood test or imaging study required to confirm it. A doctor or pain specialist will typically rely on a history of shingles, the location and character of the pain, and its duration (persisting 90 days or more from rash onset) in the same dermatome. Because the diagnosis depends heavily on timing, it’s genuinely useful for patients to keep a rough note of when the rash first appeared and how the pain has changed since.

Can PHN Be Prevented?

Prevention efforts focus on two evidence-backed strategies:

  • Early antiviral treatment: Starting acyclovir, valacyclovir, or famciclovir within 72 hours of the rash appearing is standard practice, particularly for anyone over 50, anyone immunocompromised, or anyone with facial/eye involvement. This reliably reduces the severity and duration of acute shingles; its effect specifically on preventing PHN is better supported for reducing acute severity than as a guaranteed PHN preventive, and results across studies vary.
  • Vaccination: The recombinant zoster vaccine is the most effective long-term tool for preventing both shingles and its complications, including PHN, and is worth discussing with a physician for eligible adults, particularly those over 50.

Treatment Options for Post-Herpetic Neuralgia

There is no single cure for PHN, and treatment is generally approached in a stepped fashion — starting with medication, adding topical options, and moving to interventional pain procedures when pain remains inadequately controlled or medication side effects become difficult to tolerate.

Medications (First-Line)

  • Gabapentinoids (gabapentin, pregabalin) — reduce nerve-signal overactivity
  • Tricyclic antidepressants (amitriptyline, nortriptyline) — reduce pain-signal transmission, used at low doses for pain rather than depression
  • Prescription pain relievers — used selectively and cautiously for more severe pain

Topical Treatments

  • Lidocaine 5% patches, applied directly over the painful area — a widely used first-line topical option, though evidence for its effectiveness is mixed across studies
  • Topical capsaicin, for localized pain relief

Interventional Pain Procedures

When medications and topical treatments haven’t brought pain to a manageable level — or when side effects outweigh the benefit — published interventional strategies for PHN include targeted nerve blocks, image-guided injections, and radiofrequency-based techniques designed to interrupt or dampen the pain signal at its source. Within Nexus Advanced Pain Management’s own interventional services, the options most relevant to PHN care include:

  • Sympathetic Nerve Block — targets the nerves associated with the affected dermatome to reduce pain signaling
  • Transforaminal Blocks — deliver targeted anti-inflammatory medication close to the affected nerve root
  • Radiofrequency Ablation — used in select, carefully evaluated cases to reduce nerve-driven pain signaling for longer-lasting relief
  • Spinal Cord Stimulation — generally considered for pain that has not responded adequately to other interventional and medical options

Whether any of these is appropriate depends on the individual patient’s pain pattern, duration, prior treatment response, and overall health — this is a decision made through in-person evaluation, not a one-size-fits-all protocol.

Common Mistakes to Avoid

  • Waiting too long to start antiviral treatment once shingles is suspected — the 72-hour window matters
  • Assuming that all lingering pain after shingles is “just healing” without tracking how it changes over the following weeks
  • Relying solely on over-the-counter pain relief for pain that is burning, stabbing, or touch-sensitive, which typically responds better to nerve-pain-specific medications
  • Delaying a pain-specialist evaluation once pain has clearly passed the 3-month mark, since earlier intervention is generally easier to manage than long-established PHN

Practical Action Plan

If shingles pain is approaching or has passed the 3-month mark, a reasonable next step is a focused conversation with a physician or pain specialist. It can help to bring:

  • The approximate date the shingles rash first appeared
  • A description of how the pain has changed — better, unchanged, or worse — over the past several weeks
  • A list of any medications already tried, including over-the-counter options
  • Notes on how the pain affects daily activities like sleep, dressing, or work

Nexus Advanced Pain Management Expert Summary

Post-herpetic neuralgia is best understood as a timeline, not a switch: ordinary shingles pain that fades over the first few weeks is part of normal healing, while pain that persists 90 days or longer in the same band of skin meets the clinical definition of PHN and is unlikely to resolve as quickly on its own. Age, acute pain severity, rash severity, and immune status are the clearest predictors of who is more likely to be affected. Early antiviral treatment and vaccination remain the best prevention tools, while treatment for established PHN follows a stepped approach — medication and topical care first, with interventional pain procedures available for patients whose pain doesn’t respond adequately to those first steps.

How Nexus Advanced Pain Management Can Help

For patients whose nerve pain has continued well beyond the healing of a shingles rash, Nexus Advanced Pain Management offers a structured, evidence-based evaluation to determine where a patient’s pain sits on this timeline and which treatment approach fits their situation. Depending on individual assessment, this may include:

  • A detailed pain assessment to confirm the pattern is consistent with PHN
  • Coordinated medication management for nerve-related pain
  • Sympathetic nerve blocks and transforaminal injections for patients whose pain has not responded adequately to medication
  • Radiofrequency ablation or spinal cord stimulation, considered selectively for longer-standing or harder-to-manage pain
  • Ongoing, personalized follow-up to adjust the treatment plan as pain responds

The goal of evaluation is always a plan matched to the individual patient — there is no guaranteed outcome or fixed protocol, and every recommendation follows an in-person clinical assessment.

Key Takeaways

  • Shingles pain is generally classified as PHN once it persists 90 days or more after the rash first appears.
  • About 1 in 5 people with shingles develop PHN; risk rises sharply with age.
  • Burning, stabbing, or touch-triggered pain confined to the old rash area is the hallmark of PHN.
  • Early antiviral treatment (within 72 hours of rash onset) and the zoster vaccine are the strongest prevention tools available.
  • Treatment typically starts with medication and topical options before moving to interventional procedures.
  • Pain that has persisted for many months is less likely to resolve without treatment, making earlier evaluation generally more manageable.
  • No two cases of PHN are identical — treatment decisions depend on individual evaluation, not a fixed formula.

Frequently Asked Questions

How long after shingles does post-herpetic neuralgia start?

PHN is defined as pain persisting 90 days or longer from the onset of the shingles rash. Pain that continues in the 30–90 day window is still within the range where it may resolve on its own.

Is it normal to still have pain a few weeks after the shingles rash clears?

Yes — some lingering discomfort in the first several weeks is common as the skin and nerves finish healing. It’s pain that persists largely unchanged at the 3-month mark that fits the definition of PHN.

Does everyone who gets shingles develop PHN?

No. Estimates suggest roughly 1 in 5 people with shingles go on to develop PHN, with the risk rising substantially with age and other factors such as acute pain severity and immune status.

Can post-herpetic neuralgia go away on its own?

For many patients, PHN improves gradually over time. However, pain that has persisted for many months (sometimes described clinically as “well established” PHN) is less likely to resolve without treatment, which is why ongoing pain is worth evaluating rather than waiting out indefinitely.

What does post-herpetic neuralgia pain feel like?

Patients typically describe burning, stabbing, or electric-shock-like pain confined to the area of the original rash, often with heightened sensitivity to light touch (allodynia).

Can the shingles vaccine prevent post-herpetic neuralgia?

The recombinant zoster vaccine is the most effective available tool for reducing the risk of both shingles and its complications, including PHN, and is generally recommended for eligible adults, particularly those over 50.

When should I see a pain specialist for shingles nerve pain?

It’s reasonable to seek a focused evaluation once pain has persisted close to or beyond the 3-month mark, is not improving, or is significantly affecting sleep and daily activities — earlier evaluation is generally easier to manage than long-established pain.

Are there non-medication treatments for post-herpetic neuralgia?

Yes. Alongside oral and topical medications, interventional options such as nerve blocks, targeted spinal injections, and radiofrequency-based procedures are established parts of PHN care when medication alone isn’t enough.

Categories Shoulder Pain

Shoulder Pain at Night: Causes and Treatment Options

Shoulder pain at night showing nighttime discomfort, shoulder inflammation, and difficulty sleeping

Quick Answer

Shoulder pain at night can happen because an irritated shoulder is placed under pressure while you sleep, particularly when lying on the painful side. Common causes include rotator cuff problems, bursitis or tendinopathy, frozen shoulder, shoulder impingement and arthritis. Night pain alone cannot identify the cause. If pain repeatedly wakes you, is getting worse, limits movement or is accompanied by weakness, swelling or an injury, a professional assessment can help determine what is actually causing it.

Quick Summary

  • Nighttime shoulder pain is a symptom with several possible causes.
  • Sleeping directly on a painful shoulder can increase pressure on irritated tissues.
  • Rotator cuff disorders, frozen shoulder, bursitis/tendinopathy, impingement and arthritis are common considerations.
  • Supporting the affected arm and avoiding direct pressure may make sleeping more comfortable.
  • Treatment depends on the diagnosis and may include activity modification, medicines, exercise/physical therapy and selected injections.
  • Persistent sleep-disrupting pain, weakness or loss of movement should be evaluated rather than repeatedly self-treated.
  • Sudden severe pain after injury, deformity, inability to move the arm, or chest/breathing symptoms require urgent medical attention.

Introduction

Shoulder pain can feel surprisingly different at night. A mild ache during the day may become strong enough to wake you when you turn in bed or lie on one side. This does not necessarily mean the condition has suddenly become more serious. Changes in sleeping position, pressure on sensitive tissues and the reduced distraction of daytime activity can make an existing problem much more noticeable. At the same time, recurring night pain can be an important clue that an underlying shoulder condition needs assessment.

Why Does Shoulder Pain Get Worse at Night?

Several factors can contribute. Lying directly on the affected shoulder can compress already irritated tissues. The position of the arm can also place stress on tendons, the bursa or the joint. When you are lying still for a prolonged period, stiffness may become more noticeable. Some shoulder conditions, particularly rotator cuff disorders and frozen shoulder, are also commonly associated with pain that disturbs sleep.

Importantly, night pain does not identify one specific diagnosis. A clinician usually considers the full pattern: where the pain is felt, which movements reproduce it, whether there is weakness or stiffness, whether there was an injury, and how long the symptoms have been present.

Common Causes of Shoulder Pain at Night

Rotator Cuff Problems

Rotator cuff tendinopathy, inflammation or a tear can cause aching shoulder pain that becomes worse at night. Pain with reaching or lifting the arm and weakness can provide additional clues. A rotator cuff problem may develop gradually through overuse or age-related tendon changes, or follow an injury.

Bursitis and Tendinopathy

Inflammation or irritation around the shoulder can become more uncomfortable when the affected area is compressed during side sleeping. Tendon-related pain may also increase with overhead activity or repeated use.

Frozen Shoulder

Frozen shoulder, or adhesive capsulitis, causes pain and progressive stiffness. Night pain can be prominent, and difficulty moving the arm in several directions is an important feature.

Shoulder Impingement

Shoulder impingement describes irritation involving tissues around the shoulder, often producing pain with lifting the arm. Pain can also be worse while sleeping, particularly on the affected side.

Arthritis

Shoulder arthritis can cause pain, stiffness and reduced function. Symptoms may be present both during activity and at rest, and advanced joint changes can interfere with sleep.

Referred or Less Common Causes

Pain felt around the shoulder can sometimes originate outside the shoulder, including from the neck. Rarely, shoulder-area pain can accompany conditions involving the chest or other parts of the body. This is one reason persistent, unusual or associated symptoms should be assessed rather than self-diagnosed.

How to Sleep With Shoulder Pain

For mild or recently developed symptoms, a few practical changes may reduce nighttime discomfort:

  • Avoid sleeping directly on the painful shoulder.
  • Try sleeping on your back or on the opposite side if comfortable.
  • Use a pillow to support the affected arm so it is not hanging unsupported.
  • Consider a semi-upright position if lying flat is uncomfortable.
  • Temporarily reduce activities that clearly aggravate the shoulder.
  • Use heat or cold only in a way that feels appropriate for your symptoms and protects the skin.
  • Use pain medicines only according to the product instructions and your clinician’s advice, particularly if you have other medical conditions or take other medicines.

These steps can improve comfort, but they do not establish the cause of persistent shoulder pain.

How Is Nighttime Shoulder Pain Diagnosed?

Diagnosis generally starts with a medical history and physical examination. The clinician may assess shoulder movement, strength, tenderness and the movements that reproduce symptoms. Imaging such as an X-ray, ultrasound or MRI may be considered when the history and examination suggest a structural problem or when symptoms persist or follow an injury. The appropriate test depends on the suspected cause.

Treatment Options

Conservative and Non-Surgical Care

Treatment should match the underlying problem rather than the time of day when pain occurs. Depending on the diagnosis, care may include activity modification, appropriate pain medication, physical therapy, mobility work and progressive strengthening. Many shoulder conditions can be managed without surgery, but the specific plan should be based on examination and clinical findings.

When Injections May Be Considered

In selected patients, an injection may be considered when pain or inflammation is limiting sleep and function despite appropriate initial care. The target and type of injection depend on the suspected pain generator, such as a joint or bursa. An injection should be considered as part of an overall treatment plan rather than as a substitute for diagnosis and rehabilitation.

When Surgery May Be Considered

Surgery is not automatically required because shoulder pain is worse at night. It may be considered for selected structural injuries, advanced joint disease or symptoms that remain significantly disabling despite appropriate non-surgical management. The decision depends on the diagnosis, severity, functional limitations and response to prior treatment.

When Should You See a Doctor?

Consider a professional evaluation if nighttime shoulder pain repeatedly wakes you, continues to worsen, persists despite reasonable home care, or is associated with weakness, significant stiffness or loss of movement. An assessment is particularly important after a fall or other injury.

Seek urgent medical attention for severe shoulder pain with an obvious deformity, sudden major swelling or inability to move the arm after injury. Shoulder pain accompanied by chest pain/pressure, difficulty breathing, sweating or other concerning symptoms can require emergency assessment because the pain may not be coming from the shoulder itself.

Nexus Advanced Pain Management Expert Summary

Nighttime shoulder pain deserves attention when it becomes recurrent or starts affecting sleep and daily function. The key point is that night pain is a symptom, not a diagnosis. Rotator cuff disorders, frozen shoulder, bursitis, tendinopathy, impingement and arthritis can produce similar complaints, while neck-related or referred pain can sometimes mimic a shoulder problem. A focused clinical assessment helps distinguish these possibilities and guides treatment. For many patients, management can begin with non-surgical measures such as activity modification, rehabilitation and appropriate pain control, with other interventions considered when clinically indicated.

How Nexus Advanced Pain Management Can Help

Nexus Advanced Pain Management provides shoulder pain evaluation and pain-management care in Ahmedabad. Its shoulder pain service describes assessment of different possible causes before selecting treatment, with non-surgical care considered where appropriate. Depending on the diagnosis, the clinic lists medication management, targeted injections, rehabilitation-oriented care and selected interventional options among its services. The appropriate treatment should be determined after a clinical evaluation rather than from nighttime symptoms alone.

Key Takeaways

  • Shoulder pain at night has multiple possible causes and should not be self-diagnosed from night pain alone.
  • Rotator cuff problems, bursitis/tendinopathy, frozen shoulder, impingement and arthritis are important considerations.
  • Changing sleep position and supporting the affected arm may reduce pressure and improve comfort.
  • Persistent pain, weakness or restricted movement warrants assessment.
  • Treatment is diagnosis-dependent and often begins with non-surgical care.
  • Urgent symptoms after injury or symptoms suggesting a cardiac problem need prompt medical attention.

Frequently Asked Questions

Why does my shoulder hurt more at night?

Pressure from sleeping position, reduced movement and an underlying shoulder condition can make symptoms more noticeable at night. Rotator cuff disorders and frozen shoulder are among conditions commonly associated with nighttime pain.

What is the most common cause of shoulder pain at night?

There is no single cause for every person. Rotator cuff-related problems, bursitis/tendinopathy, frozen shoulder, impingement and arthritis are common possibilities.

How should I sleep with shoulder pain?

Avoid putting direct pressure on the painful shoulder. Try the opposite side or your back and use pillows to support the affected arm. A semi-upright position may help some people.

Can a rotator cuff problem cause pain at night?

Yes. Rotator cuff injuries and tendon disorders commonly cause pain that can worsen at night, sometimes together with weakness or pain during overhead movement.

Can frozen shoulder cause nighttime pain?

Yes. Frozen shoulder commonly causes pain and stiffness, and the pain may be worse at night and disturb sleep.

When should I see a doctor for shoulder pain at night?

Arrange an evaluation when pain repeatedly disrupts sleep, persists or worsens, limits movement, or is associated with weakness. Seek urgent care after significant injury or for severe symptoms.

Can shoulder pain at night be treated without surgery?

Many shoulder conditions can initially be managed with non-surgical approaches such as activity modification, appropriate medication, physical therapy and selected injections. The right approach depends on the diagnosis.

Could shoulder pain actually come from the neck?

Yes. Some neck-related nerve problems can refer pain toward the shoulder. A clinical assessment can help distinguish a shoulder problem from referred pain.

Can I use pain medicine before bed?

Some people use over-the-counter pain medicines for short-term symptom relief, but suitability depends on medical history, other medicines and the specific product. Follow label directions and seek clinician or pharmacist advice when unsure.

Is nighttime shoulder pain an emergency?

Usually not by itself. Emergency assessment is warranted when shoulder pain occurs with concerning chest or breathing symptoms, or when severe pain follows an injury with deformity, major swelling or inability to move the arm.

Categories PRP Therapy

PRP Recovery Timeline: Week-by-Week Guide

PRP recovery timeline showing the expected stages of recovery after platelet-rich plasma injection

Quick Answer

PRP recovery does not follow one fixed schedule for everyone. After a platelet-rich plasma injection, some people experience temporary soreness, swelling or stiffness before symptoms gradually improve. Recovery can take several weeks or longer depending on the condition treated, the tissue involved and the rehabilitation plan.

A useful general framework is to think about recovery in stages: the first few days focus on protecting the treated area, the following weeks involve gradual movement and rehabilitation, and later stages focus on progressive strengthening and return to normal activities.

Quick Summary

  • Mild soreness, swelling or bruising can occur after PRP.
  • The first week is generally focused on protecting the treated area.
  • Activity should usually increase gradually rather than immediately returning to strenuous exercise.
  • Rehabilitation may become an important part of recovery.
  • Improvement may take several weeks, particularly for musculoskeletal conditions.
  • Tendon, muscle and joint problems can have different recovery patterns.
  • A temporary change in pain does not by itself determine whether PRP has worked.
  • Your treating clinician’s instructions should take priority over a generic timeline.

Introduction

Platelet-rich plasma, commonly called PRP, is an injection prepared from a patient’s own blood. Platelets are concentrated and then delivered to a targeted area with the aim of supporting the body’s healing response. PRP is used in several musculoskeletal conditions, although evidence and expected outcomes vary depending on the condition being treated.

One of the most common questions after treatment is: “What should I expect each week?”

The answer is more nuanced than a simple countdown. PRP recovery is influenced by the treated tissue, the underlying condition, the injection approach and the rehabilitation programme. The timeline below is therefore a general framework rather than a promise of when a particular patient will recover.

What Happens After a PRP Injection?

The injection introduces concentrated platelets into the treatment area. These platelets contain biological substances involved in tissue repair and healing. However, the exact mechanism and clinical effect of PRP are not completely understood, and results can differ between conditions.

Some patients experience temporary discomfort after the injection. Soreness, swelling or bruising around the injection site can occur.

This early period should not be interpreted as the final treatment result.

PRP Recovery Timeline: Week by Week

Recovery periodWhat may happenGeneral focus
Days 1–3Soreness, swelling or tenderness may occurProtect the treated area
Week 1Early discomfort may gradually settleGentle movement as advised
Weeks 2–4Function may gradually improveBegin or progress rehabilitation
Weeks 4–8Strength and activity may gradually increaseProgressive loading
Week 8+Further improvement may occurGradual return to higher activity


Days 1–3: Initial Recovery

The first few days are often focused on managing the immediate effects of the injection. You may notice local soreness, mild swelling, tenderness, bruising or temporary stiffness. During this period, avoid assuming that feeling better or worse means the treatment has succeeded or failed. Early symptoms are not a reliable measure of the eventual result. Follow the activity and medication instructions provided by your treating clinician.

Week 1: Protecting the Treated Area

During the first week, the goal is generally to avoid unnecessary stress on the treated tissue while maintaining appropriate movement. Depending on the treatment site, your clinician may recommend gentle movement or range-of-motion exercises. However, strenuous exercise, heavy lifting or high-impact activity may need to be restricted temporarily. Do not copy another patient’s PRP protocol simply because they received treatment for a similar problem.

Weeks 2–4: Gradual Return to Movement

As early discomfort settles, rehabilitation may become more important. Depending on the condition, this stage may involve gentle mobility exercises, gradual walking or daily activity, range-of-motion work, isometric exercises, supervised physical therapy and controlled strengthening. The key principle is progressive loading rather than sudden loading.

Weeks 4–8: Progressive Rehabilitation

For many musculoskeletal conditions, recovery continues beyond the initial few weeks. If your clinician considers the treated tissue ready, rehabilitation may progress toward greater resistance, improved strength, better movement control, increased activity tolerance and condition-specific exercises. This stage should be based on functional progress rather than the calendar alone.

Week 8 and Beyond: Returning to Higher Activity

Some patients may continue to improve beyond eight weeks. The timing of a return to running, sport, heavy resistance training or other demanding activities depends on the original diagnosis and the tissue treated. Therefore, week 8 should not be treated as an automatic clearance date. A safer approach is to progress activity when symptoms, function, strength and clinical assessment indicate that the tissue is ready.

What Affects PRP Recovery Time?

  1. The condition being treated — different conditions respond differently to PRP.
  2. The tissue involved — tendon, muscle, ligament and joint problems have different biological and functional demands.
  3. Severity of the problem — more significant tissue damage may require longer rehabilitation.
  4. Rehabilitation — the right progression of exercises can be an important part of recovery.
  5. Overall health and activity level — individual patient factors can influence recovery.
  6. PRP preparation and treatment protocol — PRP is not one standardized product or procedure.

For this reason, online recovery timelines should be used for general education rather than as personal medical instructions.

What Should You Avoid After PRP?

Your clinician’s instructions should take priority, but patients are commonly advised to avoid activities that place excessive stress on the treated area during the early recovery period. Depending on the treatment, this may include:

  • High-impact exercise
  • Heavy lifting
  • Aggressive stretching
  • Returning immediately to competitive sport
  • Activities that significantly aggravate symptoms

Medication advice can also vary. Some clinicians recommend avoiding NSAIDs because of concerns about their effects on the inflammatory response, while protocols differ between practices. Do not start, stop or change medication without discussing it with your healthcare provider.

When Should You Contact Your Doctor?

Contact your healthcare provider if you develop symptoms that are unexpected, severe or progressively worsening. Particular attention is warranted for:

  • Severe or increasing pain
  • Significant swelling
  • Fever
  • Increasing redness or warmth
  • Drainage from the injection site
  • New weakness, numbness or neurological symptoms
  • Any other symptom that concerns you

PRP injections are generally considered to have a relatively low risk of serious complications, but bleeding, infection, tissue damage and nerve injury are recognized risks.

How Rehabilitation Supports PRP Recovery

PRP should not automatically be viewed as a standalone solution. For many musculoskeletal conditions, the treatment plan may combine the injection with activity modification and rehabilitation. The purpose is not simply to wait for the injection to work but to progressively restore appropriate movement, strength and function.

The right rehabilitation programme depends on the diagnosis.

Expert insight: The most useful question is often not “What week am I in?” but “Has my function improved enough to safely progress?” This allows activity to be adjusted according to actual recovery rather than an arbitrary calendar date.

Nexus Advanced Pain Management Expert Summary

PRP recovery is best understood as a gradual process rather than a fixed week-by-week guarantee. Temporary soreness or swelling can occur after treatment, while meaningful improvement may take several weeks or longer depending on the condition and tissue treated.

Patients should avoid judging treatment success too early and should follow the rehabilitation plan provided by their healthcare professional.

Most importantly, recovery should be guided by the diagnosis, symptoms, functional progress and clinical assessment—not simply by the number of weeks since the injection.

How Nexus Advanced Pain Management Can Help

At Nexus Advanced Pain Management, PRP treatment can be considered as part of an individualized pain-management approach when clinically appropriate.

A professional assessment can help determine whether PRP is relevant to the underlying condition, what other treatment options may be appropriate, and how activity or rehabilitation should be progressed after treatment.

The focus should remain on understanding the source of pain, selecting an appropriate treatment strategy and monitoring recovery over time.

Key Takeaways

  • PRP recovery does not follow one identical timeline for every patient.
  • Early soreness, tenderness or swelling can occur after an injection.
  • The first week generally requires protection of the treated area.
  • Activity should usually progress gradually.
  • Rehabilitation may play an important role in restoring function.
  • Tendon, muscle and joint treatments can have different recovery patterns.
  • Improvement may take several weeks or longer.
  • Do not use a generic online timeline as personal medical clearance.
  • Contact your healthcare provider if symptoms are severe, worsening or concerning.
  • Your treating clinician’s post-PRP instructions should take priority.

Frequently Asked Questions

How long does PRP take to work?

There is no universal timeframe. Results can become noticeable after several weeks for some joint applications, while the overall response depends on the condition and treatment area.

Is pain normal after a PRP injection?

Some soreness, tenderness or bruising can occur after PRP. However, severe or progressively worsening pain should be discussed with your healthcare provider.

Can I exercise after PRP?

Activity restrictions vary according to the treated condition and tissue. High-impact or strenuous activity is commonly limited during early recovery, followed by gradual rehabilitation when appropriate.

When can I return to sports after PRP?

There is no universal return-to-sport date. It depends on the injury, symptoms, strength, functional progress and rehabilitation plan.

Does PRP recovery take longer for tendon problems?

It can. Tendons and other tissues have different healing and loading characteristics, so recovery should be individualized rather than based on a single standard timeline.

Should I take anti-inflammatory medicines after PRP?

Medication instructions vary. Some PRP protocols recommend avoiding NSAIDs because of their potential effects on inflammation, but you should follow the specific instructions given by your treating clinician.

What happens if I feel better after only one week?

Early improvement does not necessarily mean that tissue recovery is complete. Continue following the recommended rehabilitation and activity progression.

When should I contact my doctor after PRP?

Seek medical advice if you experience severe or worsening pain, significant swelling, fever, increasing redness, drainage, new neurological symptoms or another concerning change.

Categories Arthritis

Early Signs of Knee Arthritis You Shouldn’t Ignore

Early signs of knee arthritis showing knee pain, stiffness, swelling and reduced movement

Quick Answer

Early signs of knee arthritis include activity-related pain that comes and goes, morning stiffness lasting under 30 minutes, occasional grinding or clicking (crepitus), mild swelling after activity, and a feeling of tightness after sitting for long periods. These symptoms can appear years before an X-ray shows advanced joint damage. Doctors use the Kellgren-Lawrence (KL) grading system, ranging from Grade 0 (normal) to Grade 4 (severe), to classify severity. Recognizing these signs early — particularly after age 40, with a family history of arthritis, or with a lifestyle involving frequent squatting or floor-sitting — allows non-surgical options to be considered before cartilage loss advances further.

Quick Summary

  • Early knee arthritis usually starts as intermittent, activity-related pain, not constant pain
  • Morning stiffness lasting under 30 minutes is typical of early osteoarthritis; longer stiffness may suggest a different joint condition
  • Crepitus (grinding or clicking) is more meaningful when paired with pain, not on its own
  • Indian population studies estimate knee osteoarthritis affects roughly 22% to 39% of adults over 40, with higher rates in women
  • Floor-sitting, squatting, and cross-legged postures common in many Indian households place extra mechanical load on the knee joint
  • The Kellgren-Lawrence (KL) system (Grades 0-4) is the clinical standard for staging knee arthritis on X-ray
  • Non-surgical treatment tends to be most effective when started at KL Grade 1-2, before significant cartilage loss
  • Delaying evaluation for six months or longer is a common reason patients present at a more advanced stage

Introduction

Knee pain is often dismissed as a normal part of aging or a temporary strain from overuse. But when discomfort, stiffness, or a subtle change in how your knee moves keeps returning, it may be one of the earliest signs of knee osteoarthritis — the most common form of arthritis affecting the joint. Population studies in India suggest knee osteoarthritis affects a substantial share of adults over 40, with prevalence estimates ranging from roughly 22% to 39% depending on the region and study. Because early symptoms are often mild and intermittent, many people wait months or years before seeking an evaluation. Recognizing the early warning signs — and understanding when they warrant a professional opinion — is one of the most useful things a patient can do for their long-term joint health.

Symptoms: The Early Warning Signs

Early knee arthritis symptoms tend to be subtle and easy to explain away. The seven most clinically recognized early signs are:

  • Activity-related pain — a dull ache during or after walking, climbing stairs, or long car rides, that improves with rest
  • Morning stiffness — knee stiffness lasting a few minutes up to 30 minutes after waking or after sitting for a while
  • Crepitus — grinding, clicking, or popping sensations when bending or straightening the knee
  • Mild swelling — a puffy or “fuller” feeling around the kneecap, especially after activity
  • Reduced range of motion — difficulty fully bending or straightening the knee compared to before
  • Tenderness to touch — discomfort when pressing along the joint line
  • Intermittent pattern — pain that comes and goes over weeks or months rather than being constant

Expert Insight: In early-stage knee osteoarthritis, symptoms are often described by patients as “coming and going for six months” rather than being present every day. This intermittent pattern is itself a diagnostic clue — constant, unchanging pain from day one is less typical of early degenerative arthritis and may point toward a different cause.

Causes

Knee osteoarthritis develops when the protective cartilage cushioning the joint gradually wears down, causing the bones to move with less cushioning between them. Over time, this can lead to changes such as bone spurs (osteophytes) and thinning of the joint space. Contributing causes include natural wear from years of joint use, previous knee injury (such as a ligament or meniscus tear), repetitive high-load activity, and joint misalignment. Unlike rheumatoid arthritis, which is autoimmune and inflammatory in origin, osteoarthritis is primarily a mechanical, wear-related process, though inflammation still plays a role in symptoms like swelling.

Risk Factors

Certain factors increase the likelihood of developing knee arthritis earlier or more severely:

  • Age over 40, with risk increasing significantly after 50
  • Female gender — Indian studies consistently show higher prevalence in women, particularly after menopause
  • Excess body weight, which increases mechanical load on the knee joint
  • Previous knee injury or surgery
  • Family history of osteoarthritis
  • Occupations or routines involving frequent squatting, kneeling, or floor-sitting
  • Sedentary lifestyle combined with periods of high joint load
  • Diabetes and hypertension, which have been associated with higher osteoarthritis risk in Indian population studies

Local Relevance: Everyday postures common in many Indian households — sitting cross-legged, squatting for floor-based tasks, and using Indian-style toilets — place the knee in deep flexion for extended periods. Research on Indian populations has specifically identified floor-based toilet use as a associated risk factor for knee osteoarthritis, alongside obesity and diabetes.

Diagnosis

A pain specialist typically begins with a clinical history and physical examination — checking for tenderness, swelling, crepitus, and range of motion — followed by weight-bearing X-rays to assess the joint space and bone changes. Severity is classified using the Kellgren-Lawrence (KL) grading system, the most widely used radiographic staging method for knee osteoarthritis:

KL GradeFindingsWhat It Generally Means
Grade 0No radiographic featuresNormal knee joint
Grade 1Doubtful joint space narrowing; possible tiny osteophytesVery early, often subtle changes
Grade 2Definite osteophytes; mild joint space narrowingEarly-to-mild osteoarthritis
Grade 3Moderate osteophytes; definite joint space narrowingModerate osteoarthritis
Grade 4Large osteophytes; severe joint space narrowing; bone changesSevere osteoarthritis

In some cases, blood tests or an MRI may be used to rule out inflammatory conditions like rheumatoid arthritis or to assess soft tissue in more detail.

Treatment Options

Treatment is guided by symptom severity, KL grade, and how much the condition affects daily function. Options range from conservative, non-surgical approaches at earlier stages to more advanced interventional or surgical options for advanced disease. The goal at every stage is realistic symptom relief and functional improvement, not a permanent cure, since cartilage changes cannot be fully reversed.

Non-Surgical Treatment Options

For patients identified at KL Grade 1-3, a range of non-surgical, evidence-based approaches may be considered as part of a personalized treatment plan, which may include:

  • Structured physiotherapy and targeted strengthening of the muscles supporting the knee
  • Weight management to reduce joint load
  • Activity modification and joint protection techniques
  • Oral or topical anti-inflammatory medication, used judiciously
  • Image-guided injections, such as corticosteroid or viscosupplementation, in appropriate cases
  • Regenerative approaches such as PRP (platelet-rich plasma) therapy, considered on a case-by-case basis
  • Radiofrequency ablation for select patients with chronic knee pain not responding to first-line measures

These approaches are discussed and tailored individually; not every option is appropriate for every patient, and outcomes vary based on severity, overall health, and adherence to the treatment plan.

Prevention Tips

  • Maintain a healthy body weight to reduce joint loading
  • Stay active with low-impact exercise such as walking, swimming, or cycling
  • Strengthen the quadriceps and hamstring muscles to support the knee joint
  • Limit prolonged squatting, floor-sitting, or deep knee flexion where possible
  • Use supportive footwear and avoid high-impact activity on hard surfaces
  • Address previous knee injuries with proper rehabilitation rather than ignoring them

Recovery and Rehabilitation

Recovery in the context of early knee arthritis is about functional improvement and symptom control rather than a fixed timeline. Patients who begin structured physiotherapy and lifestyle adjustments at KL Grade 1-2 often notice gradual improvement in stiffness and function over several weeks to a few months, though this varies by individual. Rehabilitation is typically an ongoing process — ongoing strength maintenance and activity modification remain relevant for long-term joint health, not just during an initial treatment phase.

Early vs Advanced Knee Arthritis: Quick Comparison

FeatureEarly Stage (KL 1-2)Advanced Stage (KL 3-4)
Pain patternIntermittent, activity-relatedFrequent or constant, even at rest
Morning stiffnessUnder 30 minutesOften longer, more pronounced
SwellingMild, after activityMore persistent, visible swelling
Range of motionSlightly reducedNoticeably limited
Typical approachNon-surgical managementMay require advanced intervention

Expert Insights

Expert Insight 1 — On Timing: Patients often wait until pain interferes with daily activities before seeking evaluation. Starting a conversation with a specialist while symptoms are still mild and intermittent generally allows for a wider range of non-surgical options to be discussed.

Expert Insight 2 — On Exercise: A common misconception is that rest is always best for early arthritis. In many cases, appropriately guided movement and strengthening are more helpful than complete inactivity, which can lead to muscle weakness around the joint.

Expert Insight 3 — On Diagnosis: Crepitus alone, without pain or swelling, is common and not necessarily a sign of arthritis. It becomes clinically relevant when it occurs alongside other symptoms such as pain, stiffness, or reduced motion.

Common Mistakes Patients Make

  • Ignoring intermittent pain for six months or longer, assuming it will resolve on its own
  • Self-medicating with painkillers long-term instead of seeking an evaluation for the underlying cause
  • Avoiding all physical activity out of fear of “making it worse,” which can weaken supporting muscles
  • Assuming knee pain always means the joint needs surgery, when many patients respond well to non-surgical care

Myths vs Facts

MythFact
Knee arthritis only affects the elderlyIndian studies show a rising trend of knee osteoarthritis presenting in adults in their 30s and 40s
Cracking or clicking knees always means arthritisOccasional joint noise without pain is common and not necessarily arthritis
Surgery is the only real treatmentMany patients at earlier stages are managed with non-surgical approaches
Exercise will worsen knee arthritisAppropriate low-impact exercise generally supports joint function rather than harming it
Once diagnosed, nothing can be doneSymptom management and functional improvement are realistic goals with an individualized plan

Questions Patients Forget to Ask

  • What is my current KL grade, and what does it mean for my treatment options?
  • Which activities should I modify, and which are still safe to continue?
  • How will we track whether treatment is working over time?
  • Are there specific strengthening exercises suited to my situation?
  • What symptoms would indicate I need to be reassessed sooner than planned?

Practical Action Plan

  1. Track your symptoms for 2-4 weeks — note when pain occurs, how long stiffness lasts, and any swelling
  2. Avoid self-diagnosing based on internet searches alone; early symptoms overlap with several other joint conditions
  3. Schedule a clinical evaluation if stiffness lasts more than 30 minutes, or pain persists beyond a few weeks
  4. Request a physical examination and, if appropriate, an X-ray to establish a baseline KL grade
  5. Discuss a personalized, non-surgical management plan before considering more invasive options
  6. Reassess periodically, since knee arthritis is a progressive condition best managed with ongoing monitoring

Nexus Advanced Pain Management Expert Summary

Early knee arthritis rarely announces itself with dramatic pain — it shows up as intermittent discomfort, brief morning stiffness, and occasional clicking that’s easy to dismiss. The most clinically useful step a patient can take is getting an accurate baseline assessment, including a KL grade, while symptoms are still mild. This is when the widest range of non-surgical, evidence-based options can be meaningfully discussed and personalized.

How Nexus Advanced Pain Management Can Help

Nexus Advanced Pain Management provides a comprehensive pain assessment for patients experiencing early or ongoing knee symptoms, including a detailed clinical history, physical examination, and imaging-based staging where appropriate. Care is organized around evidence-based treatment plans that may include non-surgical pain management, interventional pain procedures such as image-guided injections or radiofrequency ablation for suitable candidates, and personalized treatment planning based on individual severity and goals. Support also extends to long-term pain relief strategies, structured rehabilitation guidance, and lifestyle modification support aimed at protecting joint function over time. This information is provided for educational purposes; specific recommendations depend on individual clinical evaluation.

Key Takeaways

  • Early knee arthritis symptoms are often intermittent — pay attention to patterns, not just isolated episodes
  • Morning stiffness under 30 minutes, activity-related pain, and mild swelling are the most common early signs
  • The Kellgren-Lawrence (KL) grading system (0-4) is the clinical standard for staging severity
  • India-specific studies estimate knee osteoarthritis affects 22-39% of adults over 40, more often women
  • Squatting, floor-sitting, and Indian-style toilet use are documented regional risk factors
  • Non-surgical management tends to offer the widest range of options at KL Grade 1-2
  • Avoid both extremes — ignoring symptoms for months, or complete inactivity out of fear
  • A clinical evaluation with X-ray staging gives an objective baseline for decision-making

FAQ Section

1. What are the earliest signs of knee arthritis?

The earliest signs typically include activity-related pain that improves with rest, brief morning stiffness, occasional grinding or clicking, and mild swelling after activity.

2. How long does morning stiffness last with early knee arthritis?

In early-stage osteoarthritis, morning stiffness typically resolves within about 30 minutes. Stiffness lasting significantly longer may point toward a different or more advanced joint condition and should be evaluated.

3. Is knee clicking or popping always a sign of arthritis?

No. Occasional joint noise without pain or swelling is common and not necessarily a sign of arthritis. It becomes more clinically relevant when paired with pain, stiffness, or swelling.

4. Can knee arthritis be reversed?

Cartilage changes associated with osteoarthritis cannot be fully reversed. However, symptoms can often be managed effectively, and functional improvement is a realistic goal with an individualized treatment plan.

5. How is knee arthritis diagnosed?

Diagnosis typically involves a clinical history, physical examination, and weight-bearing X-rays, which are used to stage severity using the Kellgren-Lawrence (KL) grading system.

6. At what age does knee arthritis usually start?

While risk increases significantly after age 50, Indian population studies have noted a rising number of patients presenting with knee osteoarthritis in their 30s and 40s.

7. Should I stop exercising if I notice early knee arthritis symptoms?

Not necessarily. Appropriately guided, low-impact exercise and strengthening often support joint function, while complete inactivity can weaken the muscles that support the knee.

8. Why is knee arthritis more common in women, especially in India?

Research consistently shows higher prevalence in women, particularly after menopause, which is associated with changes in cartilage metabolism. Structural and lifestyle factors may also contribute.

9. Does squatting or floor-sitting cause knee arthritis?

Frequent deep-knee postures such as squatting, cross-legged sitting, and floor-based toilet use have been identified as associated risk factors in Indian population studies, likely due to the additional mechanical load placed on the joint.

10. When should I see a pain specialist for knee pain in Ahmedabad?

Consider a clinical evaluation if knee pain or stiffness persists beyond a few weeks, if morning stiffness lasts more than 30 minutes, or if symptoms begin affecting daily activities like walking or climbing stairs.

11. What non-surgical treatments are available for early knee arthritis?

Options may include physiotherapy, weight management, activity modification, medication, image-guided injections, and in select cases, PRP therapy or radiofrequency ablation, tailored to individual severity and goals.

12. Is knee arthritis the same as rheumatoid arthritis?

No. Knee osteoarthritis is primarily a mechanical, wear-related condition, while rheumatoid arthritis is an autoimmune, inflammatory condition. They require different diagnostic and treatment approaches.

Categories Slip Disc/Sciatica Pain

Difference Between Slip Disc and Sciatica: Symptoms, Causes & How to Tell Them Apart

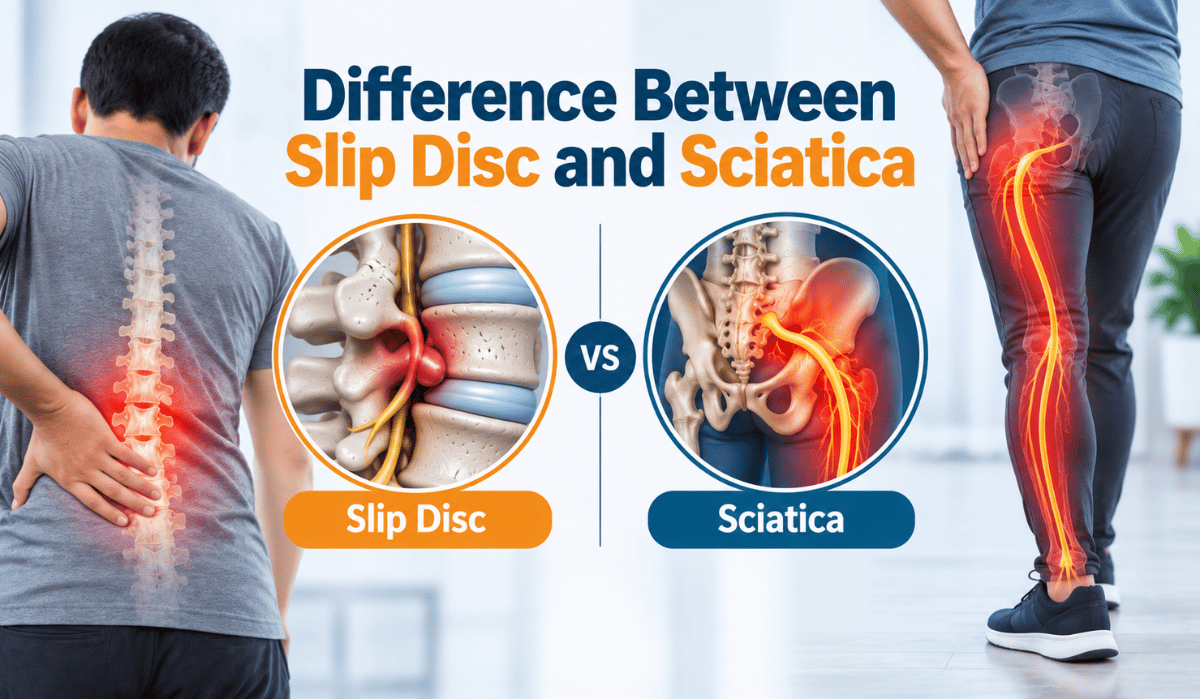
Difference between slip disc and sciatica showing a herniated disc and sciatic nerve pain symptoms

Quick Answer

A slip disc (herniated or prolapsed disc) is a structural problem in the spine, where the cushion between two vertebrae bulges or ruptures. Sciatica is not a disease by itself — it is a pattern of nerve pain that travels along the sciatic nerve, from the lower back through the buttock and down the leg. A slip disc is one of the most common causes of sciatica, but sciatica can also occur without any disc problem, and a slip disc does not always cause sciatica. The distinction matters because it changes how the condition is diagnosed and treated.

Quick Summary

  • A slip disc is a condition affecting the spinal disc; sciatica is a symptom of nerve irritation, not a disease on its own.
  • A slip disc can occur without ever causing sciatica — many disc bulges are found on scans without any nerve symptoms.
  • Sciatica can also happen without a slip disc, caused instead by piriformis syndrome, spinal stenosis, or spondylolisthesis.
  • Slip disc pain is often localized to the back; sciatica pain travels along a specific nerve path into the buttock, leg, or foot.
  • Doctors use tests such as the straight-leg-raise test and dermatome mapping, alongside history and examination, before considering an MRI.
  • Most sciatica improves within four to six weeks with conservative, non-surgical care.
  • Warning signs such as saddle numbness or new bladder or bowel changes need urgent medical attention, regardless of the underlying cause.

Introduction

If you have lower back pain that shoots down your leg, you have probably already searched online and found two terms used almost interchangeably: slip disc and sciatica. This confusion is understandable — the two conditions overlap often enough that even the pain pattern can feel identical. But they are not the same thing, and understanding the difference genuinely changes how a doctor evaluates and treats you. This guide breaks down what each condition actually is, how they relate to each other, how they are diagnosed, and what evidence-based, non-surgical treatment options typically look like.

What Is a Slip Disc?

A slip disc, medically called a herniated, prolapsed, or ruptured disc, occurs when the soft inner core (nucleus pulposus) of a spinal disc pushes out through a tear in its tougher outer layer (annulus fibrosus). It most commonly affects the lower back (lumbar spine), particularly the L4-L5 and L5-S1 discs, though it can occur in the neck as well.

Disc problems exist on a spectrum, from a mild bulge to a fully displaced fragment. Radiologists generally describe them as a bulge, protrusion, extrusion, or sequestration, depending on how far the disc material has moved and whether it has separated from the parent disc. This matters clinically because the degree of herniation often (though not always) correlates with symptom severity, and it is one of the details an MRI report will specify.

Expert Insight

“Not every slip disc seen on an MRI is the cause of a patient’s pain. Disc bulges are extremely common with age and are frequently found incidentally on scans done for unrelated reasons. This is why we always correlate imaging findings with the patient’s actual symptoms and physical examination, rather than treating the scan in isolation.”

What Is Sciatica?

Sciatica refers to pain that follows the path of the sciatic nerve — the longest and widest nerve in the body, running from the lower spine through the buttock and down the back of the leg. Sciatica is a symptom, not a diagnosis in itself. It develops when a nerve root feeding into the sciatic nerve is compressed or irritated.

A slip disc is the most common cause of sciatica, but it is far from the only one. Other causes include:

  • Spinal stenosis — narrowing of the spinal canal, more common in older adults
  • Spondylolisthesis — one vertebra slipping forward over the one below it
  • Piriformis syndrome — a deep buttock muscle spasming and irritating the nerve
  • Bone spurs or age-related degenerative changes in the spine

This is the central point most patients miss: you can have sciatica without ever having a slip disc, and you can have a slip disc without ever developing sciatica.

Key Difference: Condition vs Symptom

The clearest way to separate the two is this: a slip disc is a structural, physical injury to the spine. Sciatica is a pattern of nerve pain that can result from that injury, or from something else entirely.

AspectSlip DiscSciatica
NatureA structural spinal conditionA symptom pattern, not a disease itself
Where pain is feltOften localized to the back; may or may not radiateTravels along the sciatic nerve into buttock, leg, or foot
Common causesAge-related wear, heavy lifting, injury, repeated strainSlip disc, spinal stenosis, spondylolisthesis, piriformis syndrome
Typical patternCan be central or one-sided; worsens with bending or liftingUsually one-sided; worsens with sitting, coughing, or sneezing
DiagnosisMRI or CT imaging when clinically indicatedClinical exam, straight-leg-raise test, dermatome mapping

Symptoms

Slip Disc Symptoms

  • Localized back or neck pain, sometimes described as a deep ache
  • Pain that worsens with bending, lifting, coughing, or sitting for long periods
  • Stiffness or reduced range of motion in the spine
  • In some cases, no symptoms at all — many disc bulges are found incidentally

Sciatica Symptoms

  • Sharp, shooting, or burning pain radiating from the lower back through the buttock and leg
  • Numbness, tingling, or a ‘pins and needles’ sensation along the nerve path
  • Muscle weakness in the affected leg, or a leg that feels heavy
  • Symptoms typically affecting one side of the body

Causes

Slip disc causes typically include age-related disc degeneration, repetitive strain, improper lifting technique, sudden twisting injuries, and excess body weight placing added load on the spine. Smoking is also associated with faster disc degeneration.

Sciatica causes trace back to whatever is compressing or irritating the sciatic nerve root — most often a slip disc, but also spinal stenosis, spondylolisthesis, piriformis syndrome, or, less commonly, a spinal tumour or infection.

Risk Factors

  • Age between 30 and 50 years for disc herniation; sciatica risk rises further with age due to degenerative changes
  • Jobs involving heavy lifting, prolonged sitting, or repetitive twisting motions
  • Sedentary lifestyle with weak core and back-supporting muscles
  • Obesity, which increases mechanical load on the lower spine
  • Smoking, which accelerates disc degeneration
  • Previous back injury or a family history of spinal disc problems

Diagnosis

Diagnosis begins with a detailed history and physical examination — most cases of sciatica can be identified clinically before any imaging is needed. A doctor will typically assess:

  • Pain pattern and distribution, checked against known dermatome maps for the L4, L5, and S1 nerve roots
  • The straight-leg-raise (Lasègue’s) test — pain reproduced between roughly 30° and 70° of hip flexion suggests nerve root irritation
  • Reflexes at the knee and ankle, and muscle strength testing (for example, weakness in big-toe extension can point to an L5 issue)
  • Red-flag screening for rare but urgent causes requiring immediate care

MRI is the imaging test of choice when it is needed, but current clinical guidance is clear that imaging is not routinely required for every case of back or leg pain. It is generally reserved for red-flag symptoms, pain that fails to improve after a reasonable trial of conservative treatment, or when a procedure is being planned.

When to Seek Urgent Care

Certain symptoms need same-day medical attention regardless of whether the cause is a slip disc or something else: numbness in the saddle area (inner thighs, groin), new difficulty controlling the bladder or bowels, or rapidly worsening leg weakness. These can indicate cauda equina syndrome, a rare but time-sensitive emergency.

Treatment Options

Treatment is guided by the underlying cause, symptom severity, and how the individual is responding over time — not by the label alone. For both slip disc and sciatica, the majority of patients improve without surgery.

Non-Surgical Treatment

  • Activity modification and short-term rest from aggravating movements, while staying generally active
  • Physiotherapy focused on core strengthening, flexibility, and posture correction
  • Oral anti-inflammatory or nerve-pain medication, prescribed and monitored by a physician
  • Interventional pain procedures such as epidural steroid injections for persistent nerve-related pain
  • Radiofrequency ablation for select cases of chronic pain not responding to first-line care
  • Lifestyle changes: ergonomic adjustments, weight management, and structured exercise

Surgery is considered a later option, generally after a reasonable trial of conservative, non-surgical treatment — typically extending to three months or more — has not provided adequate relief of disabling leg pain, or if there are red-flag findings such as progressive neurological weakness.

Expert Insight

“Patients often ask whether a slip disc always needs surgery. In most cases, it does not. A structured non-surgical program — physiotherapy, activity modification, and, where appropriate, targeted interventional procedures — resolves the majority of cases. Surgery is reserved for a smaller subset where conservative care has genuinely been given a fair trial and has not worked, or where there are clear neurological red flags.”

Prevention Tips

  • Use proper lifting technique: bend at the knees and hips, not the waist, and keep the load close to your body
  • Maintain a strengthening routine for core and back-supporting muscles
  • Avoid prolonged sitting; take short movement breaks every 30 to 45 minutes
  • Maintain a healthy body weight to reduce load on the lumbar spine
  • Correct your workstation ergonomics — screen height, chair support, and desk posture
  • Avoid smoking, which is linked to faster disc degeneration

Recovery and Rehabilitation

Recovery timelines vary by individual and severity, but as a general pattern, most people with sciatica notice meaningful improvement within four to six weeks of starting conservative treatment. Slip disc recovery can take longer, particularly if physiotherapy and activity modification are needed to rebuild strength and prevent recurrence. Gradual return to normal activity, guided rehabilitation exercises, and consistent posture habits are typically more effective for long-term outcomes than prolonged rest.

Common Mistake

Many patients either rest too much, fearing that any movement will worsen a slip disc, or return to heavy activity too soon once the sharp pain fades. Both approaches can slow recovery. Prolonged bed rest weakens supporting muscles, while premature heavy lifting can trigger a flare-up before the disc and nerve have adequately healed.

Expert Insight: On Imaging and Overtreatment

A frequent concern we see is patients requesting an MRI at the very first visit, assuming imaging will immediately clarify everything. In reality, MRI findings such as disc bulges are extremely common in people with no pain at all, so an image alone can be misleading without a matching clinical picture. A careful history and examination remain the foundation of an accurate diagnosis, with imaging used selectively rather than as a first step for everyone.

Common Mistakes Patients Make

  • Assuming any back pain that travels to the leg is automatically a slip disc, when several other conditions can cause identical sciatica symptoms.
  • Skipping physiotherapy because the pain has temporarily eased, which increases the risk of recurrence.
  • Self-medicating with painkillers for weeks without a proper diagnosis, delaying appropriate treatment.
  • Requesting or expecting an MRI before a clinical evaluation, even when imaging is not yet indicated.
  • Believing surgery is the only real solution, when most cases respond well to non-surgical, evidence-based care.

Myths vs Facts

MythFact
A slip disc always causes sciatica.Many disc bulges or herniations are asymptomatic and cause no nerve pain at all.
Sciatica means you definitely have a slip disc.Sciatica can result from piriformis syndrome, spinal stenosis, or spondylolisthesis, with no disc involvement.
Surgery is the only permanent fix.Most patients improve significantly with structured non-surgical treatment.
Complete bed rest speeds up healing.Staying appropriately active generally supports better, faster recovery than prolonged rest.
An MRI is needed to confirm every case.Imaging is often unnecessary early on and is reserved for red flags or non-improving cases.

Questions Patients Forget to Ask

  • Is my pain coming from the disc itself, or from nerve irritation caused by something else?
  • What specific exercises should I avoid right now, and which ones are safe to continue?
  • How will we know if conservative treatment is working, and by when should I expect improvement?
  • What red-flag symptoms should prompt me to seek immediate care rather than waiting for my next appointment?
  • If imaging is recommended, how will the result actually change my treatment plan?

Practical Action Plan

  1. Track your symptoms: note where the pain is felt, whether it radiates, and what movements worsen or ease it.
  2. See a pain specialist or spine doctor for a clinical evaluation rather than self-diagnosing from symptoms alone.
  3. Stay appropriately active — avoid both complete bed rest and activities that clearly aggravate symptoms.
  4. Begin guided physiotherapy early rather than waiting for the pain to become severe.
  5. Reassess with your doctor if there is no meaningful improvement within four to six weeks, or sooner if red-flag symptoms appear.

Nexus Advanced Pain Management Expert Summary

A slip disc and sciatica are related but distinct: one is a structural spinal problem, the other is a nerve pain pattern that may or may not stem from it. Accurate diagnosis — built on a careful history, physical examination, and imaging only when genuinely indicated — is what determines the right, evidence-based treatment path. Most patients can expect meaningful improvement with structured non-surgical care.

How Nexus Advanced Pain Management Can Help

Nexus Advanced Pain Management approaches back and leg pain through a comprehensive pain assessment that looks beyond imaging alone to understand the actual source of symptoms. This includes evidence-based treatment planning tailored to whether the presentation points to a structural disc problem, nerve irritation, or both.

Care typically involves non-surgical pain management as a first line of treatment, with interventional pain procedures such as epidural injections or radiofrequency ablation considered for select patients whose symptoms persist despite conservative care. Every treatment plan is built around personalized goals, with attention to rehabilitation guidance and lifestyle modification support so that recovery is sustainable rather than temporary. The focus throughout remains on long-term pain relief strategies rather than short-term symptom masking.

Key Takeaways

  • A slip disc is a structural condition; sciatica is a nerve pain symptom, and the two do not always occur together.
  • Sciatica can arise from causes other than a slip disc, including piriformis syndrome and spinal stenosis.
  • Clinical examination, including the straight-leg-raise test, is usually the first step in diagnosis — not imaging.
  • Most cases of both slip disc and sciatica improve with structured non-surgical treatment.
  • Staying appropriately active supports recovery better than prolonged bed rest.
  • Red-flag symptoms like saddle numbness or bladder changes require immediate medical attention.
  • Surgery is reserved for cases that do not respond to an adequate trial of conservative care, or where red flags are present.

Frequently Asked Questions

Is a slip disc the same as sciatica?

No. A slip disc is a structural spinal condition, while sciatica is a pattern of nerve pain that a slip disc can cause, but does not always cause.

Can you have sciatica without a slip disc?

Yes. Sciatica can result from spinal stenosis, spondylolisthesis, piriformis syndrome, or age-related degenerative changes, without any disc herniation present.

Can a slip disc heal without surgery?

Many slip discs improve with non-surgical treatment such as physiotherapy, activity modification, and, when needed, interventional pain procedures. Surgery is considered only if conservative treatment does not provide adequate relief.

How long does sciatica usually last?

Many people notice meaningful improvement within four to six weeks of starting appropriate conservative treatment, though timelines vary by individual and cause.

What test confirms sciatica?

There is no single definitive test. Doctors combine history, physical examination findings such as the straight-leg-raise test, and dermatome assessment; imaging is used selectively rather than routinely.

Is walking good for sciatica or a slip disc?

Gentle, appropriately paced walking is generally encouraged as part of staying active, though a doctor or physiotherapist should tailor activity recommendations to your specific presentation.

When should I worry about sciatica symptoms?

Seek urgent care if you notice numbness in the saddle area, new difficulty controlling your bladder or bowels, or rapidly worsening leg weakness.

Does a slip disc always show up on an MRI?

MRI can detect most disc herniations, but many people without any pain also have disc bulges visible on MRI, so findings must be correlated with symptoms.

What is the difference between sciatica and piriformis syndrome?

Both cause similar buttock and leg pain, but sciatica from piriformis syndrome originates from muscle irritation of the nerve rather than a spinal disc problem, and often requires a different treatment focus.

Can sitting for long hours cause a slip disc or sciatica?

Prolonged sitting increases pressure on the lower spinal discs and is a recognized risk factor for both disc problems and the onset of sciatic nerve irritation.

Where can I get evaluated for slip disc or sciatica symptoms in Ahmedabad?

Nexus Advanced Pain Management provides comprehensive evaluation for back and leg pain, including assessment for slip disc and sciatica, at its Ahmedabad clinic.

Is surgery always required for a herniated disc with sciatica?

No. The majority of patients improve with non-surgical treatment. Surgery is typically reserved for cases with disabling pain that has not responded to an adequate trial of conservative care, or for specific neurological red flags.